

Comparison of the accuracy of Meridion-TORic IOL astigmatism prediction (EVO Toric formula v2.0 VS. Traditional calculator)
Comparison of the accuracy of predicting astigmatism with noon Toric IOL (EVO Toric formula v2.0 vs. traditional calculator)
In clinical practice, nearly 40% of eyes have significant astigmatism (>0.5 D), and its correction has become a common goal for cataract patients after cataract surgery. The most effective treatment option is usually implantation of Toric intraocular lens (IOL). For surgeons, preoperative planning relies on various calculators to determine the astigmatism and axial position of the Toric IOL. In the past, these calculators relied on the assumption that astigmatism mainly came from the anterior surface of the cornea. Reports from multiple researchers have shown that the average postoperative refractive astigmatism was between 0.4-0.6D, and the proportion of postoperative residual astigmatism<0.5 D was between 50% and 70%.
With the deepening understanding of corneal posterior surface astigmatism, Toric IOL has developed a method that combines corneal anterior and posterior surface astigmatism. For example, the Baylor toric nomogram corrected the measured corneal astigmatism (KA) to take into account the contribution of posterior corneal surface astigmatism (PCA); Barrett toric calculator (BTC) uses proprietary algorithms that not only consider empirically derived PCA, but also adjust astigmatism based on predicted effective crystal position (ELP). Some studies have shown that BTC is superior to traditional calculators that only consider KA. Abulafia et al. reported a predicted astigmatism error of 0.55 D using two different traditional calculators, while the predicted astigmatism error using BTC was only 0.02 D.
The EVO Toric formula v2.0 adds astigmatism correction capability to the original EVO formula, combining theoretical corneal posterior surface astigmatism prediction with thick lens modeling, and is applicable to different types of Toric IOLs. A recent study by Kane et al. shows that BTC and EVO Toric formulas have the same ability to predict astigmatism errors (see the previous relevant literature interpretation of this official account for details: "If there is dispersion, it must be corrected, and meridian helps! - Toric IOL calculation with built-in" Kane formula "), but this study has not been compared with traditional calculators.

In 2020, Professor Seth's team published an article titled "Predictability of Residual Postoperative Astigmatism After Implantation of a Toric Intrafocal Lens Using Two Different Calculator" in the journal Clinical Ophthalmology, evaluating the accuracy of EVO Toric Formula v2.0 and enVista Toric Calculator traditional calculators in predicting postoperative residual refractive astigmatism (RA).
The enVista Toric calculator is a proprietary traditional calculator based on KA vector addition and surgical induced astigmatism (SIA), which does not take into account the effective lens position (ELP) of the Toric IOL when predicting postoperative residual astigmatism.
This study is a secondary analysis of de identified data from a prospective multicenter clinical trial. The original dataset included 112 eyes from 112 patients. Due to the lack of anterior chamber depth or postoperative refractive error, 3 eyes were excluded and 109 eyes were analyzed. The comparison between the two calculators is based on 109 eyes, including 67 eyes (61.5%) with syndromic astigmatism (ATR), 38 eyes (34.9%) had retrograde astigmatism (WTR), Four eyes (3.7%) had oblique astigmatism, of which 97 eyes (89%) had implanted Toric IOLs with effective astigmatism equal to or less than 1.4 D.
research results
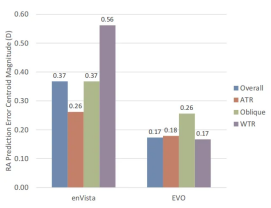
Figure 1. Residual astigmatism (RA) predicted error centroid size ATR, inverse astigmatism; WTR, conforming astigmatism; Oblique astigmatism.
The results show that the centroid of RA prediction error of the traditional calculator and the EVO calculator are 0.37D@178 and 0.17D@90 (p<0.0001), respectively, as shown in Figure 1.
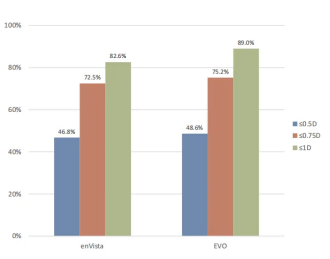
Figure 2. Proportion of residual astigmatism prediction error within the range of 0.5, 0.75, and 1.00 diopters (D)
The proportion of absolute RA prediction errors ≤ 0.5D for traditional calculators and EVO calculators is 46.8% and 48.6%, respectively (p=0.78), and the proportion of absolute RA prediction errors ≤ 1.0D is 82.6% and 89.0%, respectively (p=0.03), as shown in Figure 2. There is a difference in the proportion of absolute RA prediction error ≤ 0.5D (p=0.015) in WTR eyes, while there is no difference in the proportion of ATR eyes (p=0.75).
The proportion of RA (ATR, WTR, or inclined axis) axis positions predicted by traditional calculators and EVO calculators matching the actual RA is 62% and 78%, respectively (p=0.0029).
research conclusion
The EVO Toric formula v2.0 outperforms traditional calculators in predicting low astigmatism eyes.
As a dynamic panoramic visualization biometric instrument, the "Ziwu" provides accurate astigmatism and axial position selection for the implantation of Toric IOL in cataract surgery, whether it is the previously introduced Kane series formula for Toric IOL calculation or the latest introduced EVO series formula for Toric IOL calculation. It strives for excellence and further promotes the realization of the "precision refractive surgery era" in cataract surgery!
 references
Pantanelli SM, Kansara N, Smits G. Predictability of Residual Postoperative Astigmatism After Implantation of a Toric Intraocular Lens Using Two Different Calculators. Clin Ophthalmol. 2020 Oct 29;14:3627-3634.


| Home | Profile | Business | Information | Responsibility | Careers | Contact Us |
| About Us | Products and Solutions | News | Public Welfare Activities | |||
| Culture | Sales Network | Gallery | Medical Assistance | Campus Recruitment | ||
| Recognition | Academy | Employee Care | ||||
| Videos |


